

What helps with knee pain?
What helps with knee pain depends primarily on its cause. In cases of overuse or a minor injury, it is often sensible to temporarily reduce activities that trigger the pain, while not keeping the knee completely still without a reason. The approach may be different in osteoarthritis, meniscus injuries, ligament problems or inflammation.
The key points at a glance
- First try to determine where the pain is coming from. The location of the pain – within the joint itself, along the joint line, below the kneecap, on the inner or outer side, or behind the knee – can help narrow down the possible causes.
- Reduce the load after a recent injury. If the pain was triggered by a fall, twist or blow, avoid movements and loads that clearly make it worse.
- Complete rest is usually not necessary. If there is no more serious injury, it is generally beneficial to maintain mobility and gradually return to a level of loading that the knee tolerates well.
- Muscle strength is important in long-term problems. Adapted exercises for the muscles around the knee and hip play an important role, especially in osteoarthritis and some overuse-related problems.
- Swelling requires a little more attention. A swollen knee can accompany an injury, osteoarthritis, inflammation or an increased amount of fluid in the joint, so the way the swelling developed and how quickly it appeared are also important.
If the knee is markedly unstable after an injury, cannot be loaded normally, is severely swollen or deformed, locks, or becomes suddenly very painful, hot and red without an injury, medical assessment is needed.
Table of contents
How can you determine why your knee hurts?
Knee pain on its own does not reveal the cause. Four pieces of information are most useful for orientation: where it hurts, how the problem started, which movements trigger the pain, and whether swelling, instability or other accompanying signs are present.
The location of the pain can narrow down the possible causes considerably, but it does not allow a diagnosis on its own. Different structures in the knee can produce very similar symptoms.
How did the pain start?
The way the problem began often tells us more than the intensity of the pain itself.
- Sudden pain after a twist, fall or blow is more suggestive of an injury to the meniscus, ligaments or other structures.
- Pain that develops gradually after increased activity is more common with overuse problems.
- Long-lasting pain with stiffness, especially in older people, may be consistent with osteoarthritis.
- A suddenly hot, very painful and swollen knee without an injury requires greater caution, as the cause is not necessarily mechanical overuse or osteoarthritis.
Does the knee joint hurt, or the muscles and other tissues around it?
When someone says that their “knee hurts”, the pain is not necessarily coming from the knee joint itself. It may also come from muscles, tendons, ligaments or their attachment sites slightly above, below or beside the knee.
This distinction is also important in our practical consultations. If the pain is clearly localised in a muscle, tendon or attachment site, it makes sense to think differently than when the pain is felt deep within the joint.
Sometimes the cause is not in the knee at all. Pain can radiate from the lower back or buttock down the thigh towards or below the knee. If it is accompanied by tingling, numbness or a burning sensation, it may be related to nerve irritation or sciatica.
What triggers the knee pain?
- stairs, squatting or standing up can place more load on the front of the knee and the kneecap,
- twisting the knee can provoke symptoms in a meniscus injury,
- longer periods of walking or standing can worsen symptoms in osteoarthritis or other load-related problems,
- running or repetitive movements can irritate tendons and other soft tissues,
- pain after prolonged sitting can occur with different problems and does not by itself confirm osteoarthritis.
Also pay attention to accompanying signs
Swelling, a sensation of clicking or catching, instability, reduced mobility and warmth of the joint are additional clues that can help distinguish between possible causes.
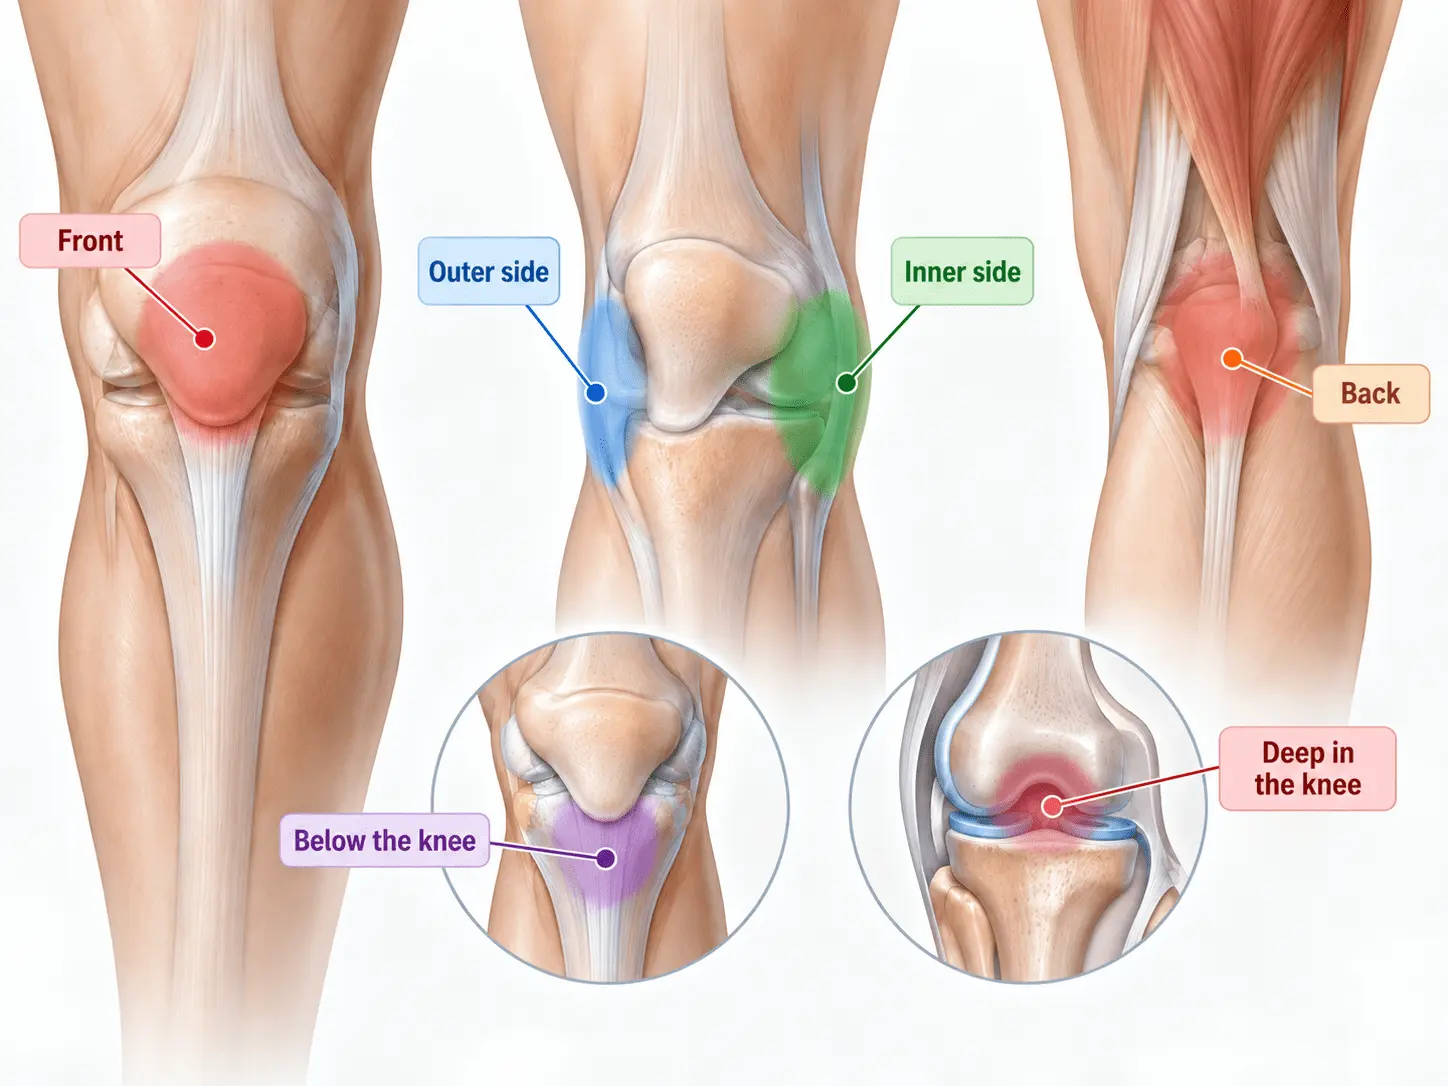
Where does the knee hurt? – front, back, inner or outer side
The location of the pain can help narrow down the possible causes, but it is not sufficient on its own to make a diagnosis. It is also important to consider how the problem started, which movement triggers the pain, and accompanying signs such as swelling, catching or instability.
Pain at the front of the knee
Pain at the front of the knee often occurs around or below the kneecap. The problem may be related to the patellofemoral joint, overuse of the patellar tendon or other structures at the front of the knee.
It is often triggered by squatting, stairs, running or prolonged sitting with the knees bent.
Pain on the inner side of the knee
On the inner side, pain may come from the medial meniscus, medial collateral ligament, tendons or the bursa slightly below the joint, or from the inner part of the knee joint itself.
If the problem started after twisting the knee and is accompanied by catching, swelling or pain with rotation, a meniscus injury is one of the possible causes.
Pain on the outer side of the knee
Pain on the outer side can be caused by the lateral meniscus, lateral collateral ligament or soft tissues along the outside of the knee. In runners and with other repetitive loading, the iliotibial band may also become irritated.
Pain behind the knee
Pain or a feeling of tightness behind the knee may come from muscles and tendons, but it may also be related to an increased amount of fluid in the joint or a Baker’s cyst.
If there is a new swelling or lump behind the knee, it is advisable to determine its cause. Sudden pain and swelling in the calf require greater caution, as the problem is not necessarily confined to the knee.
Pain below the knee
Pain just below the kneecap may be related to the patellar tendon, while pain slightly more towards the inner side may also involve the tendons and bursa in the area known as the pes anserinus.
In younger and physically active people, such problems often appear after an increase in running, jumping or other repetitive loading.
Pain deep in the knee
Pain that is difficult to localise and is felt deep within the joint can occur with various joint problems, including meniscus problems or knee osteoarthritis. Osteoarthritis is also often associated with stiffness, reduced mobility and pain with loading.
The location of the pain is therefore mainly a guide. If the problem keeps returning, lasts for a longer period or is accompanied by significant swelling, instability or locking of the knee, medical assessment is needed to determine the cause more precisely.
Most common causes of knee pain
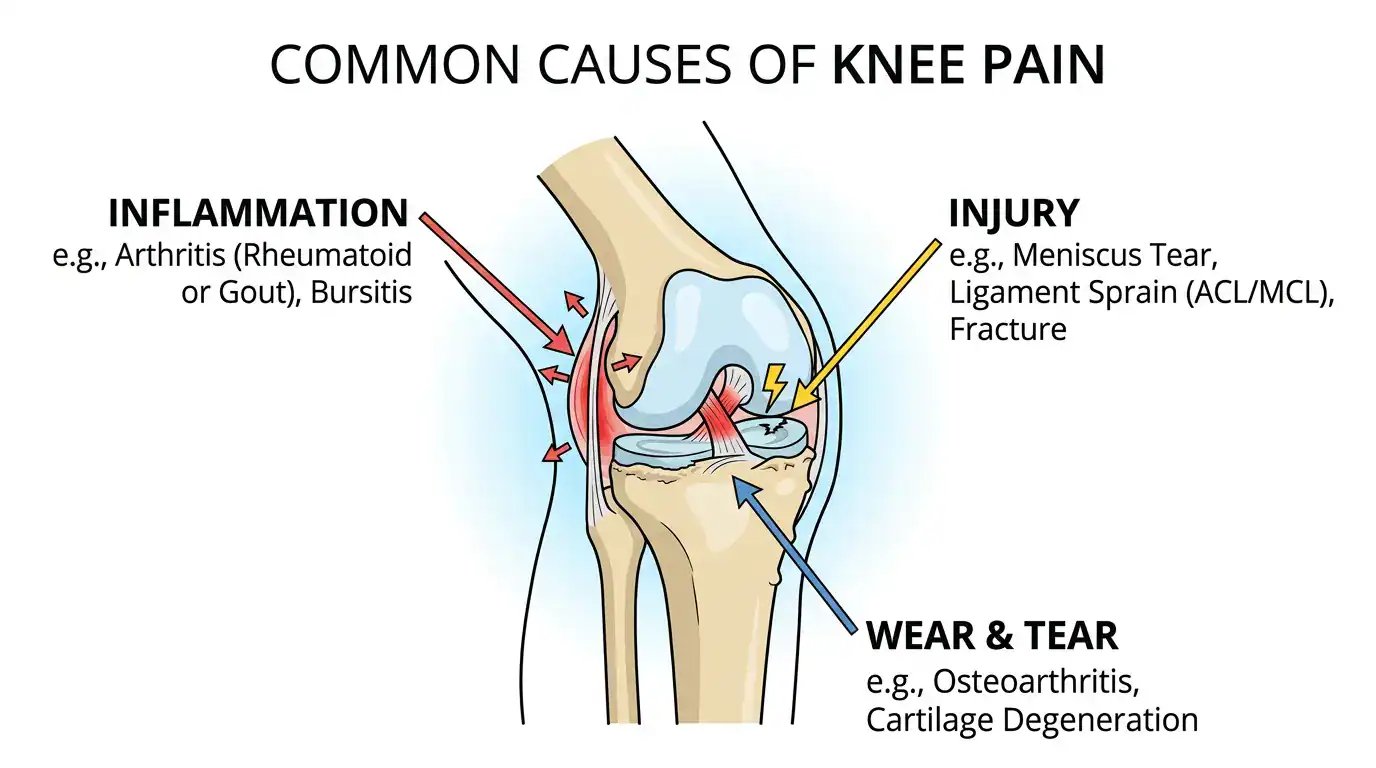
Knee pain is not a single condition. It can be caused by changes within the joint itself, injuries to the meniscus or ligaments, overloaded tendons and other soft tissues, inflammatory conditions, or pain referred to the knee from another part of the body.
Knee osteoarthritis
Osteoarthritis is a common cause of long-term problems, especially in middle and older age. Typical features include gradually developing pain with loading, brief stiffness after rest, and sometimes reduced mobility and occasional swelling.
The degree of change seen on an X-ray is not always proportional to the severity of the pain. More about what happens in the joint in osteoarthritis and what joint space narrowing means is explained on the page Osteoarthritis – symptoms, treatment and what helps.
Meniscus injury
The menisci are cartilage structures between the thigh bone and shin bone that help distribute loads within the knee. Injury can occur when the knee twists, while in older people it may also develop gradually due to degenerative changes.
Pain is often more pronounced along the joint line on the inner or outer side. Swelling, catching or a feeling that the knee is not completely reliable during certain movements may also occur.
Knee ligament injuries
Ligaments stabilise the knee joint. They can be injured by a sudden twist, fall, direct blow or sports injury.
With a more significant injury, rapid swelling and a feeling of instability or of the knee “giving way” may occur in addition to pain.
Pain around the kneecap
Pain at the front of the knee is often related to the patellofemoral area. Symptoms may be more noticeable during squatting, walking up or down stairs, running or after prolonged sitting with the knee bent.
This type of pain is not necessarily caused by osteoarthritis and is also common in younger and physically active people.
Tendons and overuse problems
Running, jumping, repeated squats or a sudden increase in sporting activity can overload tendons and other soft tissues around the knee.
In such cases, pain is often more localised above or below the joint or at a specific attachment site and becomes more pronounced when the affected structure is loaded.
Bursitis
Bursae are small fluid-filled sacs that reduce friction between tissues. If they become irritated or inflamed, localised pain and swelling may occur, for example in front of the kneecap or on the inner side slightly below the knee.
The problem may be related to prolonged kneeling, repetitive loading or injury.
Joint inflammation, gout and other conditions
Pain and swelling in the knee can also be caused by inflammatory joint diseases, gout or, more rarely, a joint infection. These conditions are not the same as ordinary mechanical overuse.
A suddenly very painful, hot, red and markedly swollen knee, especially with fever or general malaise, requires prompt medical assessment.
When the cause is not in the knee at all
Pain can also be referred to the knee area from the hip or spine. A spinal origin is more likely if the pain radiates down the leg, shifts location or is accompanied by tingling, numbness or a burning sensation.
In such cases, the source of the problem may be more important than the place where the pain is felt. More about pain of nerve origin is explained on the page Sciatica – symptoms, duration and what helps.
Meniscus: where does it hurt and what helps?
The menisci are two crescent-shaped cartilage structures between the thigh bone and shin bone. They help distribute loads within the knee and contribute to joint stability. A meniscus injury can occur suddenly when the knee twists, but it can also develop gradually due to degenerative changes.
Where does a meniscus injury hurt?
Pain is often most pronounced along the joint line on the inner or outer side of the knee, depending on which meniscus is affected. It is often triggered by twisting the knee, a deep squat or rising from a squat.
In addition to pain, swelling, catching, clicking or reduced mobility may occur. The location of the pain alone does not confirm a meniscus injury, as similar symptoms can also be caused by ligaments, tendons, osteoarthritis and other structures.
How does a meniscus injury occur?
In younger people, injury during sport or another sudden twisting movement with the knee under load is more common. In older people, the meniscus can gradually change over time and become damaged even without a clear single event.
This means that not every meniscus change seen on an MRI is necessarily the cause of pain, and not every injury requires surgery.
What helps with meniscus problems?
The approach depends on the type of injury and the symptoms. For many problems, the first step is to adapt activity, maintain mobility and gradually strengthen the muscles around the knee. Physiotherapy also has an important role in long-term or degenerative problems.
If a particular movement clearly triggers pain, it makes sense to limit it temporarily, but not to stop using the knee completely without a reason.
Can the meniscus heal on its own?
The possibility of healing depends mainly on the location, shape and extent of the injury. The outer edge of the meniscus has a better blood supply than its inner part, so some injuries have a greater chance of spontaneous healing than others.
It is important, however, to distinguish between healing of the injured structure itself and improvement in symptoms. Knee pain and function can improve even when the meniscus change remains visible on imaging.
What does “ointment for the meniscus” mean?
The term “ointment for the meniscus” is somewhat misleading. External application cannot mechanically repair a torn meniscus. Topical approaches are used primarily on the area where the person feels symptoms and can form part of a broader approach together with load adjustment and movement.
In our practical consultations, it is therefore important first to determine whether the pain is really coming from the joint area or meniscus, or from a muscle, tendon or ligament around the knee. This also influences the practical way in which Smrekovit is used.
When is medical assessment needed?
Assessment is particularly advisable after a more significant injury, with pronounced swelling or instability, and when the knee repeatedly catches or cannot be fully straightened or bent normally.
If pain persists despite adapting activity or significantly limits walking and everyday use of the knee, a more detailed assessment of the cause is advisable.
Swollen knee, fluid in the knee and Baker’s cyst
Knee swelling is an accompanying sign, not a diagnosis. It can develop after an injury, with osteoarthritis, due to inflammation of the joint or irritation of structures around the knee. What matters most is where the swelling is located, how quickly it developed, and whether the knee is also hot, red or very painful.
What does “fluid in the knee” mean?
The expression “fluid in the knee” is usually used for an increased amount of joint fluid, or a joint effusion. The knee may appear visibly enlarged, feel tight, move less easily or give a sensation of pressure.
A joint effusion can occur after an injury to the meniscus or ligaments, with active osteoarthritis, in gout and other inflammatory joint conditions, and more rarely with infection.
Swelling after a knee injury
If the knee swells after a twist, fall or blow, the cause may be an injury to the meniscus, ligaments or other structures within the joint. A larger swelling that develops quickly after an injury is an important finding and may be a reason for medical assessment.
A smaller localised swelling at the front or inner side of the knee may also come from a bursa, tendon or other soft tissues and does not necessarily represent a joint effusion.
Swelling in knee osteoarthritis
In osteoarthritis, calmer periods can alternate with periods of greater pain, tenderness and swelling. Swelling therefore does not necessarily mean that the joint has suddenly become much more “worn” within a few days, but may reflect more active processes in the joint at that time.
More about the relationship between joint wear, joint space and symptoms is explained on the page Osteoarthritis – symptoms, treatment and what helps.
Baker’s cyst – swelling behind the knee
A Baker’s or popliteal cyst is a fluid-filled swelling at the back of the knee. It often develops when there is an increased amount of fluid in the knee joint, so it can be associated with osteoarthritis, a meniscus injury or other changes within the joint.
It can cause a feeling of pressure or tightness behind the knee and make bending more difficult. It therefore makes sense to address primarily the cause of what is happening within the knee itself, not just the swelling behind it.
When is a swollen knee a reason for medical assessment?
Assessment is especially advisable if the swelling is pronounced, develops quickly after an injury, keeps returning or significantly limits movement.
A suddenly very painful, hot and red knee, especially with fever or general malaise, requires prompt medical assessment.
Caution is also needed if pain and swelling in the calf suddenly develop. A ruptured Baker’s cyst can cause symptoms similar to deep vein thrombosis, so this should not be interpreted simply as ordinary knee swelling.
If swelling is the main problem or also occurs outside the knee area, see our guide to swelling, possible causes and warning signs.
Sudden pain after a knee injury
If knee pain appears suddenly after a fall, twist, blow or sports injury, an injury to structures in or around the knee should be considered first. The most important factors are the mechanism of injury, how quickly swelling develops, knee stability and the ability to bear weight normally.
What can be injured in the knee?
A sudden injury can affect the meniscus, ligaments, tendons, muscles or bone. Pain alone therefore does not indicate which structure has been injured.
- twisting the knee can injure the meniscus or ligaments,
- a direct blow can cause soft-tissue injury, a haematoma or joint injury,
- a sudden push-off, sprint or jump can overload or injure tendons or muscles,
- a fall can cause a combination of several injuries.
What does swelling after an injury mean?
Swelling is common after an injury, but how quickly it develops and how extensive it is are important. A larger swelling that develops rapidly after a twist or fall may indicate a more significant injury within the joint.
A smaller local swelling slightly above, below or beside the knee may also come from soft tissues.
Is the knee stable?
A feeling that the knee “gives way”, buckles or is unreliable when bearing weight is an important sign. It may accompany an injury to the ligaments or another structure involved in joint stability.
The same applies to marked catching or an inability to fully straighten or bend the knee.
What should you do in the first few days after an injury?
The first step is to reduce activities that clearly increase the pain and not force the knee into movements it cannot tolerate. Complete rest is generally not necessary without a specific reason, but the level of loading should be adapted to the actual condition.
With a minor injury, the main thing to monitor is the trend – whether pain, swelling and mobility improve from day to day.
What about cooling with ice?
In our practical approach when using Smrekovit products, we do not recommend cooling with ice. Smrekovit is therefore generally used without regular simultaneous cooling of the injured area.
This is our practical method of use, based on many years of experience and advising users. We have described the reasons for this approach in more detail in the article Cooling with ice – why we do not recommend it for injuries.
When is medical assessment needed after an injury?
Medical assessment is especially advisable or necessary if:
- the knee cannot be loaded normally,
- the swelling is extensive or develops very quickly,
- the knee is markedly unstable,
- the knee locks or cannot be straightened normally,
- there is an obvious deformity,
- pain and function do not improve over the following days.
If a fracture, dislocation or more significant ligament or tendon injury is suspected, a local approach cannot replace appropriate medical care.
What helps with different causes of knee pain?
There is no single measure that is best for every type of knee pain. The approach depends on whether the problem is a recent injury, overuse, the meniscus, osteoarthritis, inflammation, or a problem in the muscles and other tissues around the joint.
Adjust the load, but do not immobilise the knee without a reason
If a particular movement or activity clearly increases the pain, it makes sense to reduce the load temporarily. This does not necessarily mean complete rest. With many problems, it is more useful to maintain movement within a range the knee tolerates well and then gradually increase the load.
Greater caution is needed after a recent injury. However, if there are no signs of a more significant injury, prolonged complete rest can lead to loss of muscle strength and even poorer knee function.
Exercises and muscle strengthening
In long-term pain, the thigh muscles, buttock muscles and other muscles involved in controlling the knee play an important role. Adapted exercises can improve strength, mobility and the knee’s ability to tolerate everyday loads.
This is particularly important in knee osteoarthritis, where therapeutic exercise and maintaining physical activity are among the core measures. If it is unclear which exercises to choose or exercise causes marked problems, a physiotherapist can adapt the programme.
For meniscus problems
Many meniscus injuries or degenerative changes are initially treated without surgery. The load is adjusted, mobility is maintained and the muscles are gradually strengthened.
Surgery is not automatically necessary simply because a meniscus injury is visible on an MRI. Symptoms and knee function are more important. The situation is different if the knee actually locks, movement is markedly restricted or there are other signs of a more significant mechanical problem.
For knee osteoarthritis
In osteoarthritis, maintaining joint function in the long term is more important than protecting the joint from every movement. Regular adapted exercise, muscle strengthening and aerobic activity are among the basic measures.
If excess body weight is present, weight loss can also reduce the mechanical load on the knee and improve symptoms.
Medicines for pain and inflammation
Pain-relieving or anti-inflammatory medicines are used for short-term symptom control in some conditions. In knee osteoarthritis, topical non-steroidal anti-inflammatory drugs in gel or cream form are among the important options.
Oral anti-inflammatory medicines are not suitable for everyone, as they can affect the stomach, kidneys and cardiovascular system and may interact inappropriately with other medicines. If they are used more frequently, it is therefore advisable to consult a doctor or pharmacist.
When is physiotherapy useful?
Physiotherapy is particularly useful when the problem lasts for a longer period, keeps returning, reduced strength or mobility remains after an injury, or when a person is unsure how to load the knee safely again.
A good programme does not consist only of passive treatments. Gradual active loading and strengthening are usually an important part of it as well.
When home measures are not enough
If the condition does not improve despite reasonable adjustment of the load, it is worth reassessing the cause. Pain that a person attributes to wear or overuse can sometimes originate from the meniscus, ligaments, hip, spine or another problem.
Medical assessment is particularly important in cases of marked instability, locking of the knee, large or recurrent swelling, and a suddenly hot and red joint.
Smrekovit for knee pain – how we approach it in practice
When advising users, we do not start only from the statement “my knee hurts”. We first try to determine whether the problem comes from the joint itself, from a muscle, tendon or ligament around it, or whether the pain is referred to the knee from elsewhere. The practical way of using Smrekovit also depends on this.
If the knee joint itself hurts
For problems that, based on the description, appear to come from the joint itself – for example confirmed osteoarthritis or long-term joint pain – our usual practical approach is Smrekovit 365 Prima together with the Smrekovit Kontakt compress.
For joint problems, the compress is an important part of the method of use because it allows the cream to remain in contact with the selected area for longer and reduces rubbing it off from the application site. If all-day use is not practical, users often use it mainly at night.
If the user does not want to use the compress, an alternative is regular repeated application. In that case, 365 Prima or 365 Ekstra can be used; with 365 Ekstra, the menthol and camphor also create a pronounced cooling sensation upon application. Smrekovit Klasik is also a possible option, but because of its greasy base it is usually less practical for frequent application to the knee.
If a muscle, tendon or ligament around the knee hurts
If the discussion suggests that the pain is not deep within the joint but is clearly localised slightly above, below or beside the knee, we approach the problem more as an injury or overuse of soft tissues.
Here too, in our practical approach, the basic choice is 365 Prima with the compress, especially for more persistent injuries. With a recent injury, it is also important to adjust the load and not massage the injured tissue.
A more detailed method of use is described in the instructions for injuries and overuse.
If the pain may be coming from the spine
We pay particular attention when the pain is not limited to the knee, but moves along the leg, is accompanied by tingling or a burning sensation, is associated with pain in the lower back or buttock, or occurs mainly in one leg.
In such cases, applying a product only to the knee often misses the source of the problem. In our practical approach, we therefore also include the spinal area. More about this type of pattern is explained on the page about sciatica and pain of nerve origin and in the instructions for use with spinal problems.
When do we expect the first change?
Based on our many years of practical experience with joint and most overuse-related problems, we ask users to assess the first result after about one week of correct and sufficiently regular use.
This does not mean that the pain must disappear within one week. We look for a clear trend: easier loading, better mobility, less tenderness or another noticeable difference. The subsequent course then depends greatly on the actual cause of the problem.
When is a local approach not enough?
Smrekovit cannot mechanically repair a torn ligament, torn meniscus, fracture or another injury that requires specific treatment. It also does not make sense to persist with local use alone if the knee locks, is markedly unstable, swells rapidly and significantly after an injury, or cannot be loaded normally.
A suddenly very painful, hot and red joint, or fever, requires medical assessment regardless of the use of a topical product.
For a more detailed practical procedure for joint problems, see the instructions for using Smrekovit on joints.
When does knee pain require medical assessment?
Most mild overuse-related problems can initially be monitored while adjusting activity. Some signs, however, increase the likelihood of a more significant injury, pronounced inflammation or another cause for which home measures are not sufficient.
When is prompt medical assessment advisable?
Prompt medical assessment is particularly important if:
- after a knee injury it is not possible to bear weight normally,
- the knee becomes very swollen very quickly,
- there is an obvious deformity,
- the knee is markedly unstable or gives way while walking,
- the knee locks or cannot be straightened or bent normally,
- the pain after an injury is very severe or the condition worsens rapidly.
A hot, red and markedly swollen knee
If the knee suddenly becomes very painful, hot, red and swollen without a clear injury, especially if fever or general malaise are also present, it should not simply be attributed to osteoarthritis or overuse.
Such a condition requires prompt medical assessment, as gout, another acute inflammatory condition or a joint infection can present in a similar way.
Calf pain and swelling
If pain and swelling of the calf suddenly occur together with problems behind the knee, caution is needed. Similar symptoms can be caused by a ruptured Baker’s cyst, but deep vein thrombosis must also be ruled out.
If the pain persists or keeps returning
Medical assessment is also advisable even without urgent warning signs if the pain does not improve despite adjusting the load, keeps returning frequently or gradually begins to limit walking, sport, work or everyday activities.
The same applies to recurrent swelling, long-lasting catching or when it is unclear whether the problem comes from the meniscus, osteoarthritis, soft tissues, the hip or the spine.
What is useful to mention during the assessment?
To help determine the cause, it is often very useful to describe exactly where it hurts, how the problem started, which movements trigger it, whether the knee swells and whether there is a feeling of instability or locking.
Imaging tests are not necessary for every case of knee pain. Whether they are appropriate depends on the course of the symptoms, the clinical examination and suspicion of a specific cause.
User experiences with knee pain
Below are individual comments from Smrekovit users who described their use of the products for knee pain or swelling. These are personal experiences of individual users; the cause of the problem, method of use and outcome vary between users.
I started using Smrekovit because I had knee pain. The X-ray did not show severe deformity, but I had been limping badly since August. Physiotherapy followed, along with the use of a topical analgesic. After speaking with a relative, I switched to Smrekovit, which I still use today, as my condition improved noticeably. I apply it to my knee twice a day and intend to continue doing so because I am very satisfied with the condition of my knee.
The user wished to remain anonymous.
[138] handwritten feedback, received 26.4.2018, stored in the Smrekovit archive
Five years ago I began to experience knee pain, followed by swelling that made it difficult for me to walk up and down stairs. I went to a doctor and a specialist and wondered what would happen with my knee. I then started using Smrekovit. I applied it 2–3 times a day, placed a compress on the knee and wrapped it with a bandage. After three to four days I began to feel a stinging sensation in the knee, then after five days small spots appeared, followed by small scabs. I stopped applying it and the scabs disappeared; the swelling and knee pain also disappeared.
Angelca, Črnomelj
[110] handwritten feedback received on 9.6.2017, stored in the Smrekovit archive
I use Smrekovit for knee pain. I applied it for one week and already noticed an improvement, so I continued using it for another fourteen days.
Slavka Godeša, Rakek
[83] handwritten feedback received on 2.11.2015, stored in the Smrekovit archive
You can find more user experiences here →
Ivo Konc’s experience with knee pain
Ivo Konc, the founder of Smrekovit, also used Smrekovit himself for decades. In the video below, he describes his experience with knee pain and how he used Smrekovit at the time.
The recording is part of the Smrekovit archive and represents the personal experience of one user, not a general guarantee of results for all knee problems.
Frequently asked questions about knee pain
What does pain on the inner side of the knee mean?
Pain on the inner side can come from the medial meniscus, medial collateral ligament, tendons or the bursa below the joint, or from the inner part of the knee joint itself. The location of the pain alone is therefore not enough to make a diagnosis. It is also important to know whether the problem started after a twist, whether the knee swells and which movements trigger the pain.
What can cause pain behind the knee?
Pain or tightness behind the knee can come from muscles and tendons, an increased amount of fluid in the joint or a Baker’s cyst. If pain and swelling of the calf also appear suddenly, medical assessment is needed, as deep vein thrombosis must also be ruled out among the possible causes.
What does a meniscus injury feel like?
Pain is often more pronounced along the joint line on the inner or outer side of the knee. It may be triggered by twisting, squatting or rising from a squat, and swelling, catching or a clicking sensation may also occur. Similar symptoms can also be caused by other structures in the knee.
Can an ointment heal an injured meniscus?
External application cannot mechanically repair a torn meniscus. Topical products are used on the area of symptoms as part of a broader approach that may include load adjustment, movement and exercises. Medical assessment is advisable in cases of pronounced knee locking, a more significant injury or persistent symptoms.
What does fluid in the knee mean?
“Fluid in the knee” usually means an increased amount of joint fluid, or a joint effusion. It can occur after an injury, with osteoarthritis, meniscus problems, gout or other inflammatory joint conditions. The cause of the effusion and how it developed are particularly important.
Is it better to rest or keep moving with a painful knee?
The level of loading should be adapted to the cause and the pain. Movements that clearly aggravate the problem should be temporarily avoided, but complete and prolonged rest is not necessary for most problems. With long-term symptoms, maintaining mobility and gradually strengthening the muscles are often an important part of management.
Should a painful knee be cooled with ice?
In our practical approach when using Smrekovit products, we generally do not recommend cooling with ice. This approach is based on our many years of practical experience and is not a universal medical rule for all injuries. More about this topic is explained in the article Cooling with ice – why we do not recommend it for injuries.
How do I know whether the pain is actually coming from the knee?
If the pain is clearly located in a muscle, tendon or slightly above or below the joint, the cause may not be in the knee joint itself. If the pain radiates from the lower back or buttock down the leg, changes location or is accompanied by tingling, numbness or a burning sensation, it may also originate from the spine or be related to sciatica.
How do we use Smrekovit for knee pain?
We first try to determine what is actually causing the pain. For problems that come from the joint itself, our usual practical approach is Smrekovit 365 Prima together with the Smrekovit Kontakt compress. If the pain comes from a muscle, tendon or ligament, or from the spine, the method of use may differ. It is described in more detail in the instructions for use with joint problems.
When should you see a doctor for knee pain?
Prompt medical assessment is advisable if the knee cannot be loaded normally after an injury, becomes rapidly and markedly swollen, is unstable or locks. A suddenly very painful, hot and red knee also requires prompt medical assessment, especially if fever or general malaise are present.